IRM – Defecografie IRM (planșeu pelvin) (MCB)
Sursă și prelucrare editorială
- Proveniență
- 1 referință declarată
- Fidelitatea preluării
- Nedocumentată
- Revizuire medicală
- Nedocumentată
Referințele declarate nu confirmă singure fidelitatea preluării sau aprobarea protocolului pentru utilizare locală.
Detalii despre surse și verificări
18 Defecography
- Ediție / versiune a sursei
- Neprecizată
- Pagină / secțiune
- Pagini: 1, 2
- Relația cu protocolul
- Document instituțional original importat integral
- Data consultării
- 2026-09-27
Prelucrarea acestei pagini
- Mod de prelucrare
- Titlu și etichete de parametri în română; textul clinic original păstrat în engleză.; Import PDF integral, imagini ale tuturor paginilor și extragere automată a parametrilor secvențelor.
- Adaptări față de sursă
- Nedocumentate; absența evidenței nu confirmă o preluare integrală.
- Responsabil pentru prelucrare
- Neprecizat
- Atribuire existentă în pagină
- MCB Radiology (documentul sursă). Această atribuire nu identifică automat autorul sursei sau revizorul medical.
- Versiunea paginii
- mcb-mri-fbc1a273594a
- Actualizare declarată a paginii
- 2026-09-27 — distinctă de revizuirea medicală.
Verificarea fidelității: Nedocumentată
Revizuirea medicală: Nedocumentată
Catalog MCB · Descarcă PDF-ul complet · Sursa MCB
Documentul MCB este disponibil integral mai jos, inclusiv notele, condițiile de utilizare a contrastului și imaginile de planificare. Textul clinic al sursei este în engleză; titlul și etichetele parametrilor sunt în română.
Protocolul original
Pagina 1

Textul paginii (engleză)
Updated 06/06/26 MRI Defecography (Pelvic Floor) Reviewed 06/06/26 Indications: fecal/urinary incontinence, constipation, urinary stasis, rectocele, cystocele, vaginal/uterine prolapse. IV contrast is not given for this protocol. Bowel preparation: NPO 4 hours prior to the exam. Exam before noon - 1 Fleets enema night before and 1 Fleets enema 1 hrs prior to the exam. Exam after noon - 1 Fleets enema 6 am morning of and 1 Fleets enema 1 hr prior to the exam. Full Pelvis FOV: Iliac crests to few slices below introitus/anus (top/bottom coverage), greater trochanter to greater trochanter (right/left coverage), anterior pelvic wall skin to posterior buttock skin (front/back coverage). Parameters for cine sequences (20 images per run, 1 image per sec). The sagittal slice for the trueFISP is midline small FOV showing the lower rectum and anal canal. The pubic symphysis should be visualized anteriorly, and the sacrum/coccyx should be visualized posteriorly. See image below. The coronal slice for the trueFISP is small FOV through the anal canal (see below image). The axial slice for the trueFISP is small FOV through the upper anal canal (see below image). First sagittal cine FISP sequences: Start with the patient in a relaxed state, then ask him/her to "squeeze" or "clench" their pelvic floor / buttocks, as if he/she is trying to perform a Kegel, or trying to stop defecating and urinating, and then relax. You should see the pelvic floor lift up during the squeeze, and then drop back down as they relax. If you don't, repeat the instructions and reimage. Subsequent sagittal cine FISP sequences: You no longer ask the patient to "squeeze" for the "push" series. Instead for each series, he/she will start in the relaxed state, and then "bear down" or "push", as he/she would try to defecate or deliver a baby. You should see the pelvic floor drop, and eventually gel should leave the rectum. If the initial "push" attempts are SUCCESSFUL, perform this "push" series with the same instructions a minimum of 3 times, then perform 1 in the axial plane, one in the coronal plane, then one more in the sagittal plane, for a total of AT LEAST 6 "push" cine series. Sometimes the patient has a hard time with the "push" series. Sometimes he/she will continue to squeeze instead of bearing down. Sometimes he/she will "bear down" appropriately and the pelvic floor will drop, but no gel will leave the rectum. Sometimes he/she will simultaneously "bear down" and "squeeze", and little or no gel might come out. Sometimes, there will be no effective pelvic floor motion during his/her attempts to push. He/she should be instructed about these issues, and you should re-explain the instructions, and reassure and try to help the patient. You should continue to repeat the push series for at least 7 unsuccessful sagittal plane tries, then proceed to the axial, coronal, and final sagittal try. If you are able to eventually get a successful push after failed attempts, then continue this "push" sagittal series with the same instructions as described above for the successful push, aiming for a minimum of 3 successful sagittal push series, then perform 1 in the axial plane, one in the coronal plane, then one more in the sagittal plane. Many patients require multiple attempts before they understand and are comfortable enough to defecate on scanner. Some patients are unable to defecate on the table no matter how many attempts they make.
Pagina 2
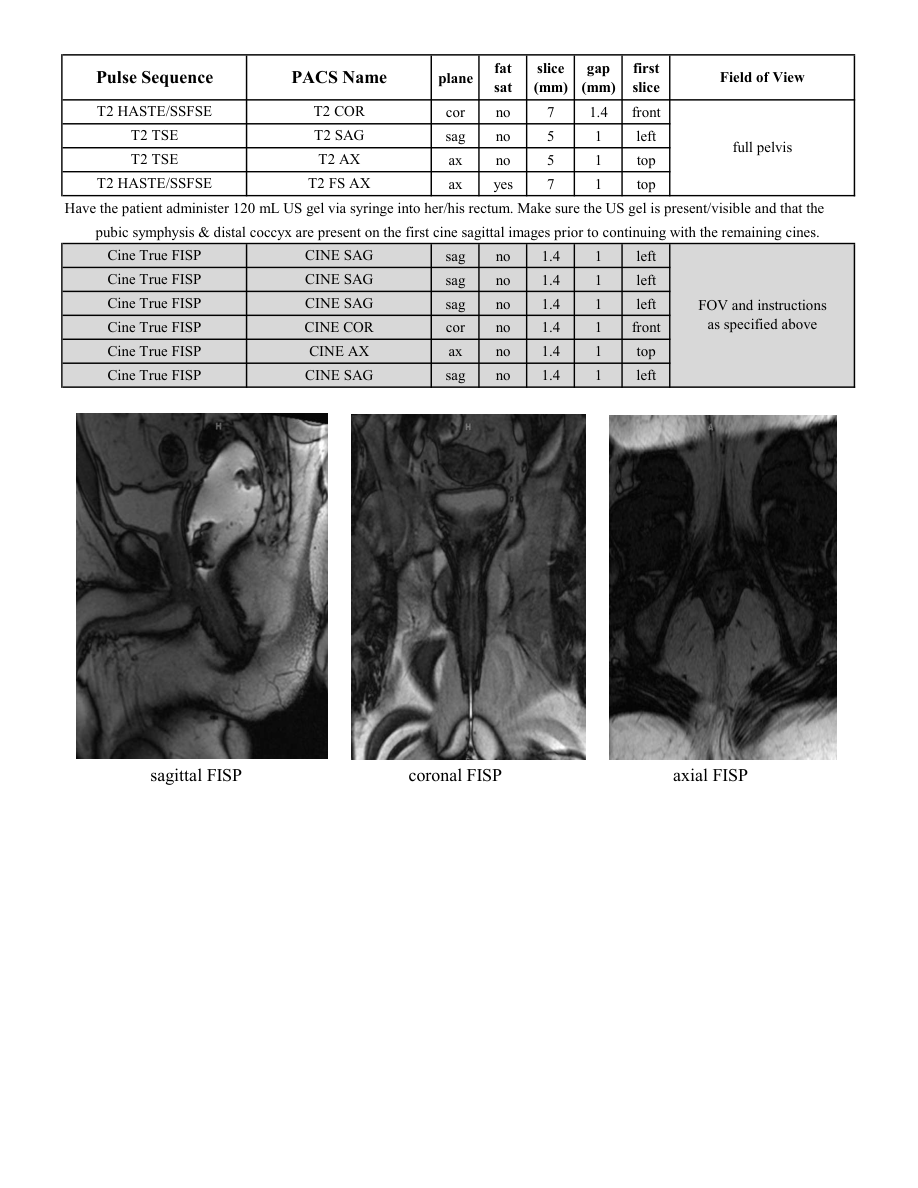
Textul paginii (engleză)
slice
gap
Pulse Sequence PACS Name Field of View plane fat
sat (mm) (mm) first
slice T2 HASTE/SSFSE T2 COR cor no 7 1.4 front T2 TSE T2 SAG sag no 5 1 left full pelvis T2 TSE T2 AX ax no 5 1 top T2 HASTE/SSFSE T2 FS AX ax yes 7 1 top Have the patient administer 120 mL US gel via syringe into her/his rectum. Make sure the US gel is present/visible and that the pubic symphysis & distal coccyx are present on the first cine sagittal images prior to continuing with the remaining cines. Cine True FISP CINE SAG sag no 1.4 1 left Cine True FISP CINE SAG sag no 1.4 1 left Cine True FISP CINE SAG sag no 1.4 1 left FOV and instructions
as specified above Cine True FISP CINE COR cor no 1.4 1 front Cine True FISP CINE AX ax no 1.4 1 top Cine True FISP CINE SAG sag no 1.4 1 left sagittal FISP coronal FISP axial FISP
gap
Pulse Sequence PACS Name Field of View plane fat
sat (mm) (mm) first
slice T2 HASTE/SSFSE T2 COR cor no 7 1.4 front T2 TSE T2 SAG sag no 5 1 left full pelvis T2 TSE T2 AX ax no 5 1 top T2 HASTE/SSFSE T2 FS AX ax yes 7 1 top Have the patient administer 120 mL US gel via syringe into her/his rectum. Make sure the US gel is present/visible and that the pubic symphysis & distal coccyx are present on the first cine sagittal images prior to continuing with the remaining cines. Cine True FISP CINE SAG sag no 1.4 1 left Cine True FISP CINE SAG sag no 1.4 1 left Cine True FISP CINE SAG sag no 1.4 1 left FOV and instructions
as specified above Cine True FISP CINE COR cor no 1.4 1 front Cine True FISP CINE AX ax no 1.4 1 top Cine True FISP CINE SAG sag no 1.4 1 left sagittal FISP coronal FISP axial FISP
Parametrii secvențelor
Tabele extrase din PDF. Variantele, secvențele condiționate și momentele administrării contrastului se citesc împreună cu notele de pe pagina originală indicată.
Tabelul 1 — pagina 2
| Secvență | Denumire PACS | Plan | Supresie grăsime | Grosime (mm) | Interval (mm) | Prima secțiune | FOV |
|---|---|---|---|---|---|---|---|
| T2 HASTE/SSFSE | T2 COR | Coronal | Nu | 7 | 1.4 | Anterior | full pelvis |
| T2 TSE | T2 SAG | Sagital | Nu | 5 | 1 | Stânga | |
| T2 TSE | T2 AX | Axial | Nu | 5 | 1 | Superior | |
| T2 HASTE/SSFSE | T2 FS AX | Axial | Da | 7 | 1 | Superior | |
| Cine True FISP | CINE SAG | Sagital | Nu | 1.4 | 1 | Stânga | FOV and instructions as specified above |
| Cine True FISP | CINE SAG | Sagital | Nu | 1.4 | 1 | Stânga | |
| Cine True FISP | CINE SAG | Sagital | Nu | 1.4 | 1 | Stânga | |
| Cine True FISP | CINE COR | Coronal | Nu | 1.4 | 1 | Anterior | |
| Cine True FISP | CINE AX | Axial | Nu | 1.4 | 1 | Superior | |
| Cine True FISP | CINE SAG | Sagital | Nu | 1.4 | 1 | Stânga |