Intervențional — Plan procedural pentru histotripsie (MCB)
Sursă și prelucrare editorială
- Proveniență
- 1 referință declarată
- Fidelitatea preluării
- Nedocumentată
- Revizuire medicală
- Nedocumentată
Referințele declarate nu confirmă singure fidelitatea preluării sau aprobarea protocolului pentru utilizare locală.
Detalii despre surse și verificări
MCB Radiology — Histotripsy Procedure Plan
- Ediție / versiune a sursei
- Neprecizată
- Pagină / secțiune
- Pagini: 1–2
- Relația cu protocolul
- Document original importat integral; atribuirea autorilor rămâne cea din PDF.
- Data consultării
- 2026-09-27
Prelucrarea acestei pagini
- Mod de prelucrare
- Titlu și navigare în română; documentul sursă în engleză.; PDF original integral, previzualizare și text extras automat; fără completarea parametrilor clinici lipsă.
- Adaptări față de sursă
- Nedocumentate; absența evidenței nu confirmă o preluare integrală.
- Responsabil pentru prelucrare
- Neprecizat
- Atribuire existentă în pagină
- MCB Radiology (portalul sursă). Această atribuire nu identifică automat autorul sursei sau revizorul medical.
- Versiunea paginii
- mcb-16d707592a93
- Actualizare declarată a paginii
- 2026-09-27 — distinctă de revizuirea medicală.
Verificarea fidelității: Nedocumentată
Revizuirea medicală: Nedocumentată
Documentul original MCB — Plan procedural pentru histotripsie
Ghid procedural · 2 pagini · consultat la 2026-09-27.
Descarcă PDF-ul integral · Sursa MCB · Catalogul MCB pentru această modalitate
Instrucțiunile, valorile și ilustrațiile din documentul original sunt păstrate în engleză. Titlul și navigarea sunt în română.
Pagina 1
Pagina 2
Textul documentului original
Pagina 1 — text în engleză
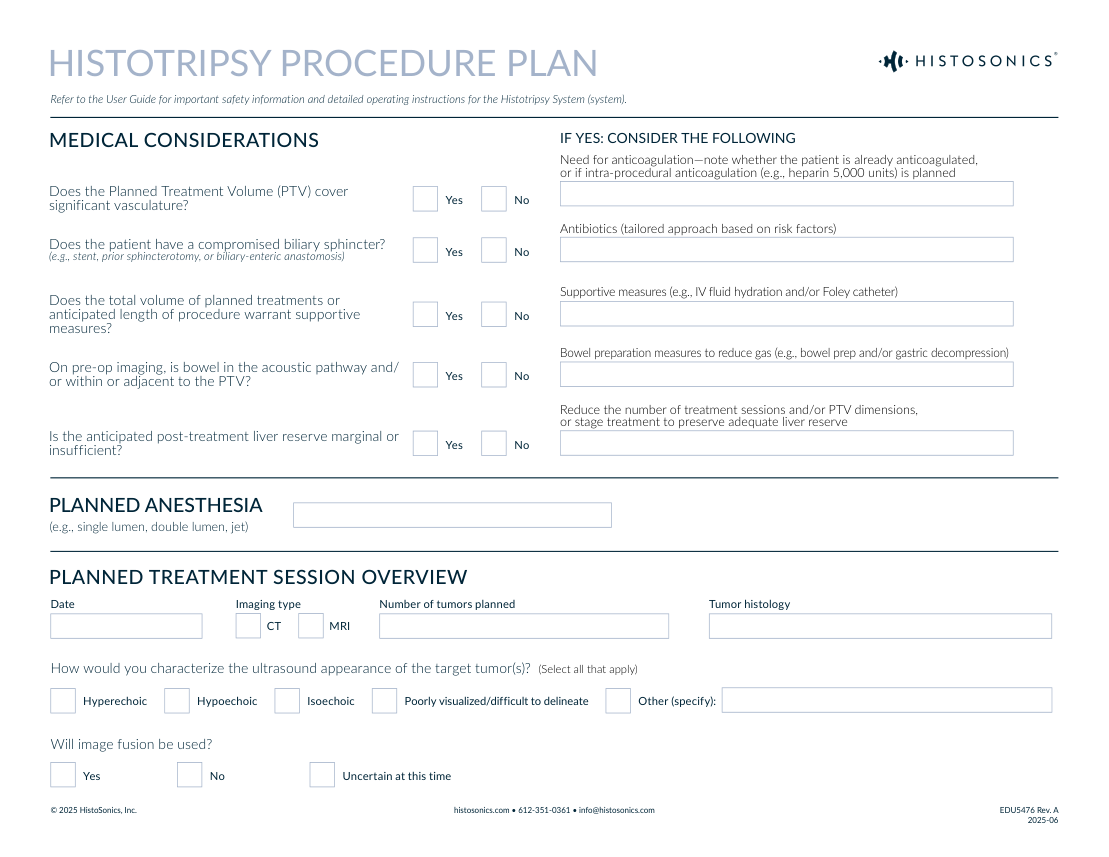
HISTOTRIPSY PROCEDURE PLAN Refer to the User Guide for important safety information and detailed operating instructions for the Histotripsy System (system). MEDICAL CONSIDERATIONS IF YES: CONSIDER THE FOLLOWING Need for anticoagulation—note whether the patient is already anticoagulated,
or if intra-procedural anticoagulation (e.g., heparin 5,000 units) is planned Does the Planned Treatment Volume (PTV) cover significant vasculature? Yes No Antibiotics (tailored approach based on risk factors) Does the patient have a compromised biliary sphincter? (e.g., stent, prior sphincterotomy, or biliary-enteric anastomosis) Yes No Supportive measures (e.g., IV fluid hydration and/or Foley catheter) Does the total volume of planned treatments or anticipated length of procedure warrant supportive measures? Yes No Bowel preparation measures to reduce gas (e.g., bowel prep and/or gastric decompression) On pre-op imaging, is bowel in the acoustic pathway and/ or within or adjacent to the PTV? Yes No Reduce the number of treatment sessions and/or PTV dimensions,
or stage treatment to preserve adequate liver reserve Is the anticipated post-treatment liver reserve marginal or insufficient? Yes No PLANNED ANESTHESIA (e.g., single lumen, double lumen, jet) PLANNED TREATMENT SESSION OVERVIEW Date Imaging type Number of tumors planned Tumor histology CT
MRI How would you characterize the ultrasound appearance of the target tumor(s)? (Select all that apply) Hyperechoic
Hypoechoic
Isoechoic
Poorly visualized/difficult to delineate
Other (specify):
Will image fusion be used? Yes
or if intra-procedural anticoagulation (e.g., heparin 5,000 units) is planned Does the Planned Treatment Volume (PTV) cover significant vasculature? Yes No Antibiotics (tailored approach based on risk factors) Does the patient have a compromised biliary sphincter? (e.g., stent, prior sphincterotomy, or biliary-enteric anastomosis) Yes No Supportive measures (e.g., IV fluid hydration and/or Foley catheter) Does the total volume of planned treatments or anticipated length of procedure warrant supportive measures? Yes No Bowel preparation measures to reduce gas (e.g., bowel prep and/or gastric decompression) On pre-op imaging, is bowel in the acoustic pathway and/ or within or adjacent to the PTV? Yes No Reduce the number of treatment sessions and/or PTV dimensions,
or stage treatment to preserve adequate liver reserve Is the anticipated post-treatment liver reserve marginal or insufficient? Yes No PLANNED ANESTHESIA (e.g., single lumen, double lumen, jet) PLANNED TREATMENT SESSION OVERVIEW Date Imaging type Number of tumors planned Tumor histology CT
MRI How would you characterize the ultrasound appearance of the target tumor(s)? (Select all that apply) Hyperechoic
Hypoechoic
Isoechoic
Poorly visualized/difficult to delineate
Other (specify):
Will image fusion be used? Yes
No
Uncertain at this time © 2025 HistoSonics, Inc. histosonics.com • 612-351-0361 • [email protected] EDU5476 Rev. A 2025-06
Pagina 2 — text în engleză
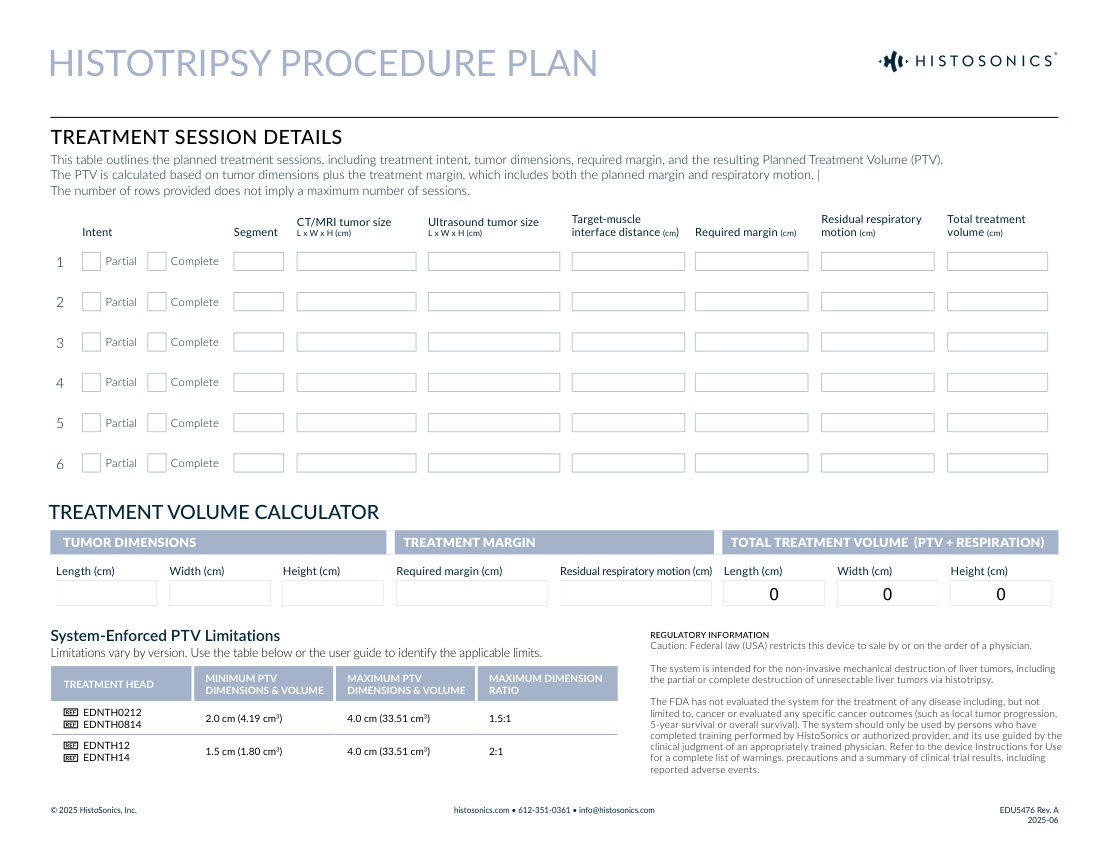
HISTOTRIPSY PROCEDURE PLAN TREATMENT SESSION DETAILS This table outlines the planned treatment sessions, including treatment intent, tumor dimensions, required margin, and the resulting Planned Treatment Volume (PTV). The PTV is calculated based on tumor dimensions plus the treatment margin, which includes both the planned margin and respiratory motion. | The number of rows provided does not imply a maximum number of sessions. Intent Segment CT/MRI tumor size L x W x H (cm) Ultrasound tumor size L x W x H (cm) Target-muscle interface distance (cm) Required margin (cm) Residual respiratory motion (cm) Total treatment volume (cm) 1 Partial Complete 2 Partial Complete 3 Partial Complete 4 Partial Complete 5 Partial Complete 6 Partial Complete TREATMENT VOLUME CALCULATOR TUMOR DIMENSIONS TREATMENT MARGIN TOTAL TREATMENT VOLUME (PTV + RESPIRATION) Length (cm) Width (cm) Height (cm) Required margin (cm) Residual respiratory motion (cm) Length (cm) Width (cm) Height (cm) 0 0 0 REGULATORY INFORMATION Caution: Federal law (USA) restricts this device to sale by or on the order of a physician. System-Enforced PTV Limitations Limitations vary by version. Use the table below or the user guide to identify the applicable limits. The system is intended for the non-invasive mechanical destruction of liver tumors, including the partial or complete destruction of unresectable liver tumors via histotripsy.
TREATMENT HEAD MINIMUM PTV DIMENSIONS & VOLUME MAXIMUM PTV DIMENSIONS & VOLUME MAXIMUM DIMENSION RATIO EDNTH0212 EDNTH0814 2.0 cm (4.19 cm3) 4.0 cm (33.51 cm3) 1.5:1 EDNTH12 EDNTH14 1.5 cm (1.80 cm3) 4.0 cm (33.51 cm3) 2:1 The FDA has not evaluated the system for the treatment of any disease including, but not limited to, cancer or evaluated any specific cancer outcomes (such as local tumor progression, 5-year survival or overall survival). The system should only be used by persons who have completed training performed by HistoSonics or authorized provider, and its use guided by the clinical judgment of an appropriately trained physician. Refer to the device Instructions for Use for a complete list of warnings, precautions and a summary of clinical trial results, including reported adverse events. © 2025 HistoSonics, Inc. histosonics.com • 612-351-0361 • [email protected] EDU5476 Rev. A 2025-06
TREATMENT HEAD MINIMUM PTV DIMENSIONS & VOLUME MAXIMUM PTV DIMENSIONS & VOLUME MAXIMUM DIMENSION RATIO EDNTH0212 EDNTH0814 2.0 cm (4.19 cm3) 4.0 cm (33.51 cm3) 1.5:1 EDNTH12 EDNTH14 1.5 cm (1.80 cm3) 4.0 cm (33.51 cm3) 2:1 The FDA has not evaluated the system for the treatment of any disease including, but not limited to, cancer or evaluated any specific cancer outcomes (such as local tumor progression, 5-year survival or overall survival). The system should only be used by persons who have completed training performed by HistoSonics or authorized provider, and its use guided by the clinical judgment of an appropriately trained physician. Refer to the device Instructions for Use for a complete list of warnings, precautions and a summary of clinical trial results, including reported adverse events. © 2025 HistoSonics, Inc. histosonics.com • 612-351-0361 • [email protected] EDU5476 Rev. A 2025-06