Ecografie — Presiuni segmentare limitate: membru inferior (MCB)
Sursă și prelucrare editorială
- Proveniență
- 1 referință declarată
- Fidelitatea preluării
- Nedocumentată
- Revizuire medicală
- Nedocumentată
Referințele declarate nu confirmă singure fidelitatea preluării sau aprobarea protocolului pentru utilizare locală.
Detalii despre surse și verificări
MCB Radiology — Leg Sementals (Limited)
- Ediție / versiune a sursei
- Neprecizată
- Pagină / secțiune
- Pagini: 1–6
- Relația cu protocolul
- Document original importat integral; atribuirea autorilor rămâne cea din PDF.
- Data consultării
- 2026-09-27
Prelucrarea acestei pagini
- Mod de prelucrare
- Titlu și navigare în română; documentul sursă în engleză.; PDF original integral, previzualizare și text extras automat; fără completarea parametrilor clinici lipsă.
- Adaptări față de sursă
- Nedocumentate; absența evidenței nu confirmă o preluare integrală.
- Responsabil pentru prelucrare
- Neprecizat
- Atribuire existentă în pagină
- MCB Radiology (portalul sursă). Această atribuire nu identifică automat autorul sursei sau revizorul medical.
- Versiunea paginii
- mcb-a57cdf70283f
- Actualizare declarată a paginii
- 2026-09-27 — distinctă de revizuirea medicală.
Verificarea fidelității: Nedocumentată
Revizuirea medicală: Nedocumentată
Documentul original MCB — Presiuni segmentare limitate: membru inferior
Protocol · 6 pagini · consultat la 2026-09-27.
Descarcă PDF-ul integral · Sursa MCB · Catalogul MCB pentru această modalitate
Instrucțiunile, valorile și ilustrațiile din documentul original sunt păstrate în engleză. Titlul și navigarea sunt în română.
Pagina 1

Pagina 2

Pagina 3

Pagina 4

Pagina 5
Pagina 6

Textul documentului original
Pagina 1 — text în engleză
PURPOSE:
To detect the presence of peripheral arterial disease and categorize the overall severity and general location using indirect testing modalities.
INDICATIONS:
Peripheral vascular disease. Claudication (pain with exertion). Rest pain. Foot or toe ulceration or gangrene. Absent palpable pulses. Suspected acute limb ischemia. Follow-up of decreased ankle-brachial index (ABI) from a previous examination. Post-operative evaluation or follow-up.-
CONTRAINDICATIONS:
Patients with suspected or known acute deep venous thrombosis (DVT) may need an examination limited to waveform analysis and use of a toe-brachial index (TBI). Any site of recent surgery, trauma, ulceration, casts or dressings that cannot or should not be compressed by pressure cuffs. Patients with incompressible arteries due to medial calcification (TBI may be used). Morbidly obese patients in whom a high-thigh pressure may be not obtainable due to increased limb girth. Patients who have significant tremors or involuntary movement may render waveform collection suboptimal or unreliable.
EQUIPMENT/SUPPLIES:
Unetixs System 3.5-10 MHz linear probe Automatic inflation device Blood pressure cuffs of varying widths and lengths
PATIENT PREPARATION & ASSESSMENT:
Introduce yourself to the patient. Verify patient identity via two patient identifiers (name and date of birth) per hospital policy. Explain the examination, its purpose and how long it will take. Answer any questions the patient may have regarding the examination. Obtain patient history including symptoms, signs, risk factors and other relevant history. Verify that the requested examination is appropriate based on the patient’s clinical presentation and history. Using Query button select patient from work list. Press the studies button on the touch-screen. The study menu will appear. Press the lower arterial history page. Leg Artery Segmental Limited Protocol – Last Updated 9/1/2024 - Page 1 of 6
Pagina 2 — text în engleză
GENERAL GUIDELINES:
A limited examination for recurring indications may be performed as indicated. Any deviations from the standard protocol and any limitations to the examination should be documented on the technologist worksheet for future reference and for repeatability in follow-up studies. Report preliminary critical findings to the referring clinician when appropriate (i.e. immediate medical attention may be warranted) and according to hospital policy.
PROPER BLOOD PRESSURE CUFF PLACEMENT: Blood pressure cuff sizes should be based on limb circumference: Arm = 12 x 44.5 cm or 10 x 44.5 cm Forearm = 12 x 44.5 cm or 10 x 44.5 cm Thigh = 12 x 44.5 cm Thigh (long) = 12 x 85 cm Calf = 12 x 44.5 cm or 10 x 44.5 cm Ankle = 12 x 44.5 cm or 10 x 44.5 cm Metatarsal = 7 x 40 cm Index Finger or Great Toe = 2.5 x 9 cm The most important technical consideration for accurate results is to make sure that the cuff is appropriately sized, tightly wrapped and in close contact with the extremity. The recommended cuff size is 20% wider than the diameter of the limb where the cuff is placed. The length of the cuff bladder should be twice its width. If the cuff is too small, it will result in erroneously high pressures. If it is too wide, the measurement will be erroneously too low. For instance, in small women and in children, it may be more appropriate to use the 10 cm cuff or even an 8 mm cuff to measure arm pressure. Accurate pressure measurements can be obtained only when the head of pressure generated by the cuff bladder can reach the artery being examined. When the bladder fails to encircle the limb, the bladder must be placed over the artery. The bladder should be placed on the posterior–medial aspect of the limb, bringing the cuff one full wrap. Then pull upward and across to tighten. In addition, the bladder must compress soft tissue not bony structures. Therefore, the below-knee cuff should be placed just distal to the tibial tubercle.
Cuffs should be placed straight rather than angled, even though the latter may better conform to the limb.
Leg Artery Segmental Limited Protocol – Last Updated 9/1/2024 - Page 2 of 6
Pagina 3 — text în engleză
DOCUMENTATION: Continuous Wave Doppler Analysis
Select Continuous wave Doppler from the Unetix arterial study menu. Care must be taken to assure the recording of the optimal signal. Sufficient acoustic gel must be used to eliminate any air between the probe and the skin.
The Doppler beam must be aligned with the long axis of the vessel. An angle of 60 degrees is usually the best angle of insonation. In the popliteal fossa an angle approaching 90 degrees to the skin may produce the optimal signal since the course of the popliteal artery is not parallel to the skin. The Doppler beam is positioned to exclude interference from the adjacent vein. Signals are optimized by sliding the transducer slowly from medial to lateral across the artery until the strongest and best signal is obtained. The transducer is then adjusted so that an approximately 45-60 degree angle with the skin is achieved. This is varied slightly so that an accurate waveform with a maximum deflection is achieved. Modest probe pressure should be used to ensure good contact while not distorting the signal. For most sites, an 8 MHz transducer permits adequate depth penetration. However, the 5 MHz probe may be used if the signal is attenuated due to depth or calcification. Gain settings should be maximized to define waveform morphology at each level.
At least three representative Doppler waveforms (i.e. cardiac cycles) are obtained (at a paper speed of 25 mm/sec) from the following arteries bilaterally:
Posterior tibial (PTA) Dorsalis pedis (DPA) Peroneal (optional)
Pulse Volume Recording Waveforms (PVR or VPR) Air plethysmographic devices record changes in segmental limb volume.
Place pressure cuffs at the following locations with the bladder of the cuff directly over the artery:
Ankle (2-3cm above the medial malleolus) Metatarsal and great toe (if appropriate) Connect the cuffs to the corresponding air hoses (right are clear, left are blue). Select Pulse Volume Recording (PVR) from the Unetix arterial study menu. Press and release the inflate button on the remote. Calibration of the cuffs is performed by the machine. Inflate each cuff to 55-65 mm Hg. Standardized inflation pressures must be used in all cuffs.
After the cuffs have stabilized, waveforms will appear on the screen. Choose satisfactory waveforms then press the capture button on your remote to freeze the screen.
Record at least three waveforms from each location. Standard of practice with this method is assessment at four levels. Otherwise you would need continuous wave Doppler to differentiate inflow from outflow disease.
If necessary, scroll to group diagnostic waveforms and press capture. This will save the waveforms and advance to the next test site. Repeat these steps for each of the remaining test sites. Press the capture button to advance to the Segmental Pressures examination.
Leg Artery Segmental Limited Protocol – Last Updated 9/1/2024 - Page 3 of 6
Pagina 4 — text în engleză
Segmental Limb Systolic Pressures
Systolic pressures obtained correspond to the vessels at the site of the pressure cuff and not to the vessel at the level of the transducer that is recording the pressure signals. Variability in systolic pressure measurements should always be considered.
Place pressure cuffs at the following locations with the bladder of the cuff directly over the artery:
Ankle (2-3cm above the medial malleolus) Great toe (if appropriate) Choose one thigh cuff for three cuff method or two thigh cuffs for four cuff method.
The Doppler transducer is positioned with the transducer directed proximally so that arterial flow will move directly into the ultrasound beam at an angle of 45-60 degrees. Care must be taken not to compress the underlying artery with the Doppler transducer. Systolic blood pressures are recorded using the Doppler transducer. Press and hold the inflate button on the remote control to inflate the intended pressure cuff. The cuff is inflated until the audible signal is no longer heard and there is no pulsatility to the waveform. In order to assure complete cessation of blood flow, the cuffs should be inflated 20-30 mmHg beyond the last audible Doppler arterial signal.
Press the deflate button once. This will slowly release the pressure from the cuff at a rate of 2-4 mmHg per second.
When the Doppler signal returns, press the capture button to record the systolic pressure.
Using the scroll return to the first deflection and press capture to advance to next segment. If pressure measurements need to be repeated, the cuff should be fully deflated for approximately one minute prior to repeat measurement. Record the systolic blood pressures for the following arteries: Right brachial Left brachial
Right dorsalis pedis artery (DPA) - Locate the dorsalis pedis artery signal on the dorsum of the foot between the first and second metatarsal heads at or proximal to the talonavicular joint. If the signal is damped, retrograde or absent at this level, move to the ankle and search for the anterior tibial signal. Right posterior tibial artery (PTA) - Look for the posterior tibial artery posterior to the tibia above the medial malleolus.
If either the DPA or the PTA is absent, the peroneal artery can be found slightly anterior to the lateral malleolus. Advance to the left extremity and obtain pressures at the same levels. The ABI is calculated by the Unetixs Multilab automatically using the highest systolic ankle pressure on each side (either dorsalis pedis or posterior tibial) divided by the higher of the two brachial pressures.
Systolic pressures are invalid in the presence of calcified, incompressible vessels and interpretation must rely on waveform analysis and toe-brachial waveforms. Leg Artery Segmental Limited Protocol – Last Updated 9/1/2024 - Page 4 of 6
Pagina 5 — text în engleză
If ABIs are unable to be obtained due to incompressible vessels proceed to TBIs (if equipment allows). If TBIs are normal the exam is complete. If TBIs are abnormal or brachial pressures are abnormal, proceed with Arterial Duplex Imaging Protocol. TBIs are calculated using the toe pressure divided by the highest brachial pressure.
CLEANING & CARE OF EQUIPMENT:
The Doppler transducer is cleaned with germicidal disinfectant wipes. All cuffs are cleaned after each examination with germicidal disinfectant wipes as per the hospital cleaning protocol. DISEASE GRADING:
Upper and lower extremity velocities and ratios:
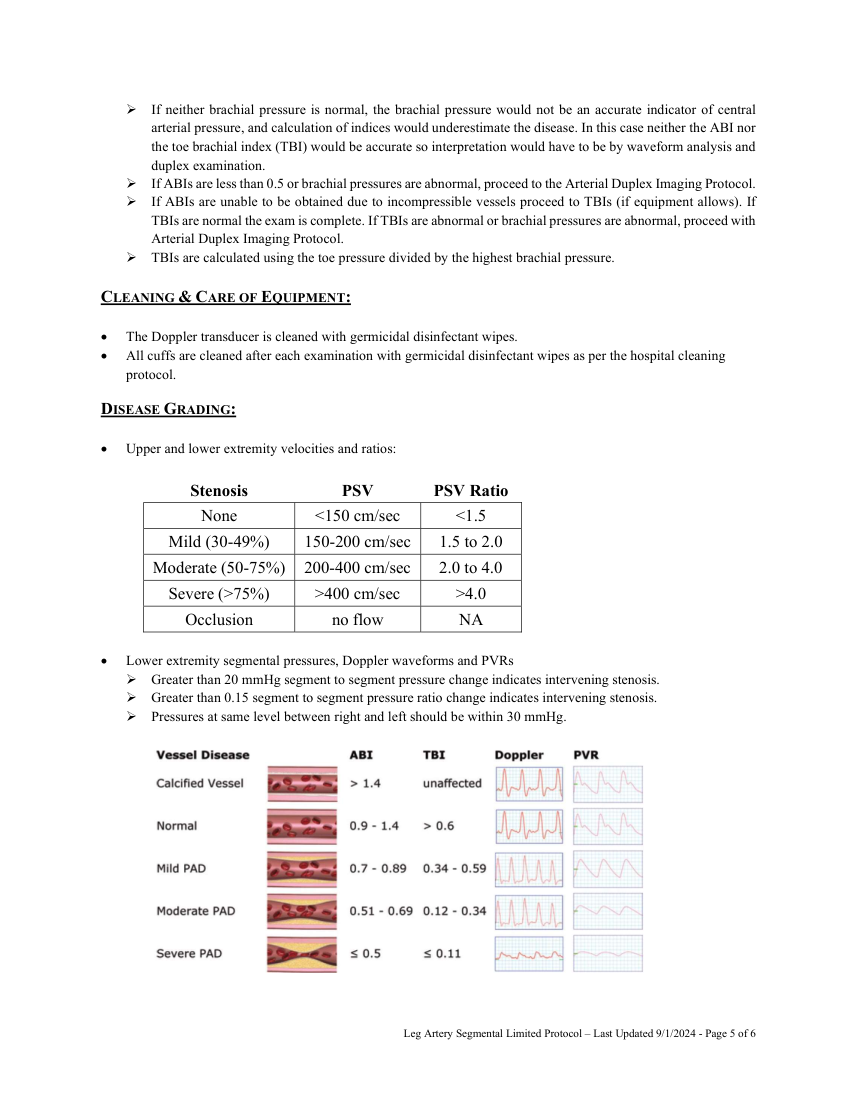
Stenosis PSV PSV Ratio None <150 cm/sec <1.5 Mild (30-49%) 150-200 cm/sec 1.5 to 2.0 Moderate (50-75%) 200-400 cm/sec 2.0 to 4.0 Severe (>75%) >400 cm/sec >4.0 Occlusion no flow NA
Lower extremity segmental pressures, Doppler waveforms and PVRs Greater than 20 mmHg segment to segment pressure change indicates intervening stenosis. Greater than 0.15 segment to segment pressure ratio change indicates intervening stenosis. Pressures at same level between right and left should be within 30 mmHg.
Leg Artery Segmental Limited Protocol – Last Updated 9/1/2024 - Page 5 of 6
Pagina 6 — text în engleză
Scissons, RP. Physiologic Testing techniques and Interpretation. Rhode Island, Unetix Educational Publishing, 2003, pp. 25-42. Sibley, Robert C., et al. “Noninvasive Physiologic Vascular Studies: A Guide to Diagnosing Peripheral Arterial Disease.” RadioGraphics, vol. 37, no. 1, 2017, pp. 346–357., doi:10.1148/rg.2017160044.
“SVU Professional Performance Guidelines.” SVU Professional Performance Guidelines - Society for Vascular Ultrasound, www.svunet.org/practicemanagementmain/professionalperformanceguidelines. Leg Artery Segmental Limited Protocol – Last Updated 9/1/2024 - Page 6 of 6