Ecografie — Artere carotide (MCB)
Sursă și prelucrare editorială
- Proveniență
- 1 referință declarată
- Fidelitatea preluării
- Nedocumentată
- Revizuire medicală
- Nedocumentată
Referințele declarate nu confirmă singure fidelitatea preluării sau aprobarea protocolului pentru utilizare locală.
Detalii despre surse și verificări
MCB Radiology — Carotid Arteries
- Ediție / versiune a sursei
- Neprecizată
- Pagină / secțiune
- Pagini: 1–4
- Relația cu protocolul
- Document original importat integral; atribuirea autorilor rămâne cea din PDF.
- Data consultării
- 2026-09-27
Prelucrarea acestei pagini
- Mod de prelucrare
- Titlu și navigare în română; documentul sursă în engleză.; PDF original integral, previzualizare și text extras automat; fără completarea parametrilor clinici lipsă.
- Adaptări față de sursă
- Nedocumentate; absența evidenței nu confirmă o preluare integrală.
- Responsabil pentru prelucrare
- Neprecizat
- Atribuire existentă în pagină
- MCB Radiology (portalul sursă). Această atribuire nu identifică automat autorul sursei sau revizorul medical.
- Versiunea paginii
- mcb-9b5279a69cd7
- Actualizare declarată a paginii
- 2026-09-27 — distinctă de revizuirea medicală.
Verificarea fidelității: Nedocumentată
Revizuirea medicală: Nedocumentată
Documentul original MCB — Artere carotide
Protocol · 4 pagini · consultat la 2026-09-27.
Descarcă PDF-ul integral · Sursa MCB · Catalogul MCB pentru această modalitate
Instrucțiunile, valorile și ilustrațiile din documentul original sunt păstrate în engleză. Titlul și navigarea sunt în română.
Pagina 1

Pagina 2

Pagina 3
Pagina 4
Textul documentului original
Pagina 1 — text în engleză
Purpose:
To evaluate the extracranial carotid and vertebral arteries to characterize plaque location, morphology and severity.
INDICATIONS:
Cerebrovascular disease. Transient ischemic attack. Cerebral infarct. Stroke symptoms. Unilateral weakness/paralysis (hemiparesis/hemiplegia). Slurred speech. Syncope. Vision changes. Carotid bruit. Status post carotid endarterectomy. Stenosis follow-up. Vertebro-basilar syndrome/insufficiency. Preoperative evaluation. Trauma. Retinal artery emboli. Giant cell arteritis. Head or neck mass.
CONTRAINDICATIONS:
Patients with bandages, casts or other hardware that precludes adequate assessment of an artery or arterial segment. Patients who are unable to cooperate due to mental status changes or involuntary movements.
EQUIPMENT:
5-7 MHz linear probe
PATIENT PREPARATION & ASSESSMENT:
Introduce yourself to the patient. Verify patient identity via two patient identifiers (name and date of birth) per hospital policy. Explain the examination, its purpose and how long it will take. Answer any questions the patient may have regarding the examination. Obtain patient history including symptoms, signs, risk factors and other relevant history.
Carotid Artery Protocol – Last Updated 9/1/2024 - Page 1 of 4
Pagina 2 — text în engleză
Optimize equipment gain and display settings with respect to depth, dynamic range and focal zones while imaging vessels. Add color Doppler to supplement grayscale images with proper color scale to demonstrate areas of high flow and color aliasing. Use power Doppler to validate low flow states or occlusions. Set spectral Doppler gains to allow a spectral window and optimized to reduce artifacts. Cursor sample size will be small and positioned parallel to the vessel wall and/or direction of blood flow. A spectral Doppler angle of 45-60 degrees or less will be used to measure velocities. Note exceptions to these angles on the technologist worksheet. The ICA/CCA ratio is calculated using the normal CCA PSV and the highest ICA PSV. Areas of suspected stenosis or occlusion will include spectral Doppler waveforms and velocity measurements recorded at and distal to the stenosis or occlusion. Sites of intervention (stents and bypass grafts) will include spectral Doppler waveforms and velocity measurements from the proximal, mid and distal aspects of the stent/graft, as well as, in the native artery just proximal to the stent/graft and in the native vessel just distal to the stent/graft. Plaque should be assessed for severity and characterized (i.e. hypoechoic, echogenic, shadowing, mixed). Send the measurements screenshot page if your machine is capable. For focal lesions (masses, cysts, nodules, lymph nodes, fibroids) obtain split-screen images of the lesion without calibers, with calibers and with Color Doppler.
Any deviations from the standard protocol and any limitations to the examination should be documented on the technologist worksheet for future reference and for repeatability in follow-up studies. Report preliminary critical findings to the referring clinician when appropriate (i.e. immediate medical attention may be warranted) and according to hospital policy.
DOCUMENTATION:
Brachial Blood Pressures Obtain blood pressures from both arms.
Grayscale Imaging Document longitudinal grayscale images of the following: Common carotid artery (CCA) proximal Common carotid artery (CCA) distal (with IMT measurement on backwall just proximal to bulb, normal thickness is ≤0.9 mm) Internal carotid artery (ICA)/bulb (also document Color Doppler image here) External carotid artery (ECA)/bulb Document transverse grayscale images of the following: Common carotid artery (CCA) proximal Carotid bulb ICA/ECA bifurcation
Spectral Doppler Waveforms Document longitudinal spectral Doppler waveforms with PSV and EDV measurements of the following: Common carotid artery (CCA) proximal
Carotid Artery Protocol – Last Updated 9/1/2024 - Page 2 of 4
Pagina 3 — text în engleză
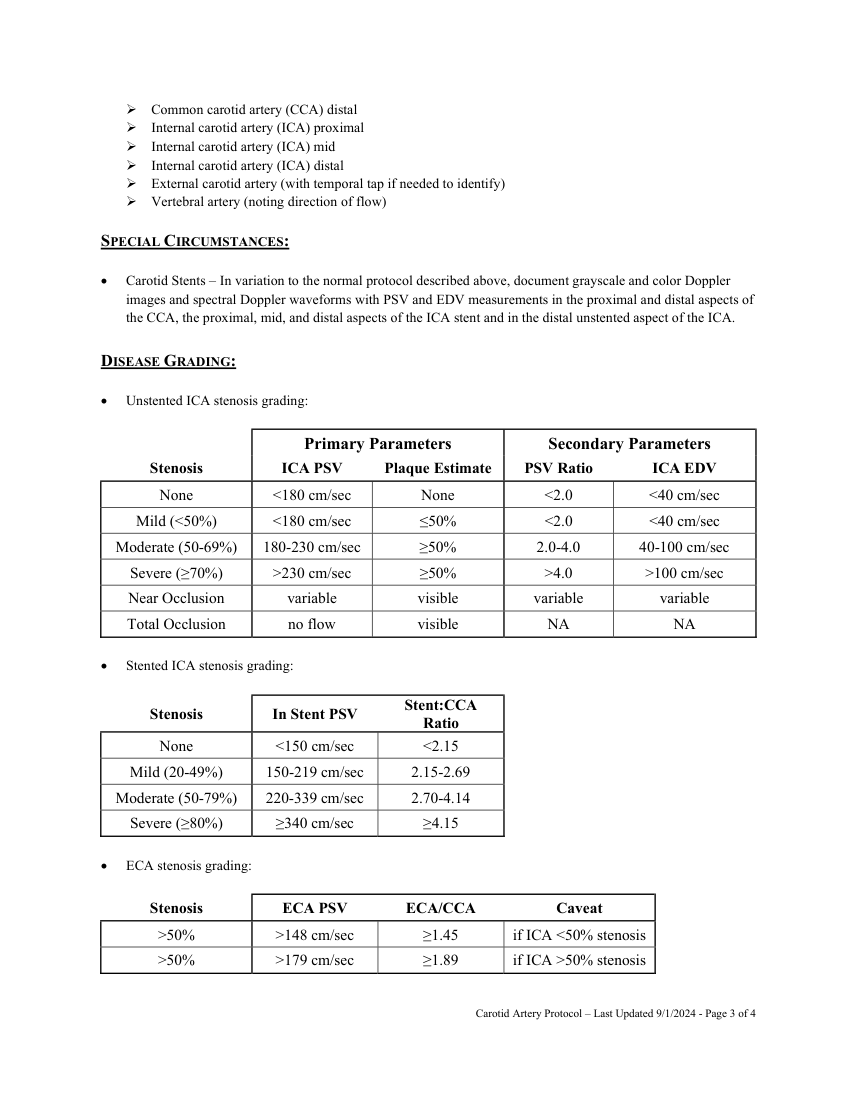
SPECIAL CIRCUMSTANCES:
Carotid Stents – In variation to the normal protocol described above, document grayscale and color Doppler images and spectral Doppler waveforms with PSV and EDV measurements in the proximal and distal aspects of the CCA, the proximal, mid, and distal aspects of the ICA stent and in the distal unstented aspect of the ICA.
DISEASE GRADING:
Unstented ICA stenosis grading:
Primary Parameters Secondary Parameters Stenosis ICA PSV Plaque Estimate PSV Ratio ICA EDV None <180 cm/sec None <2.0 <40 cm/sec Mild (<50%) <180 cm/sec ≤50% <2.0 <40 cm/sec Moderate (50-69%) 180-230 cm/sec ≥50% 2.0-4.0 40-100 cm/sec Severe (≥70%) >230 cm/sec ≥50% >4.0 >100 cm/sec Near Occlusion variable visible variable variable Total Occlusion no flow visible NA NA
Stented ICA stenosis grading:
Stenosis In Stent PSV Stent:CCA Ratio None <150 cm/sec <2.15 Mild (20-49%) 150-219 cm/sec 2.15-2.69 Moderate (50-79%) 220-339 cm/sec 2.70-4.14 Severe (≥80%) ≥340 cm/sec ≥4.15
ECA stenosis grading:
Stenosis ECA PSV ECA/CCA Caveat >50% >148 cm/sec ≥1.45 if ICA <50% stenosis >50% >179 cm/sec ≥1.89 if ICA >50% stenosis
Carotid Artery Protocol – Last Updated 9/1/2024 - Page 3 of 4
Pagina 4 — text în engleză
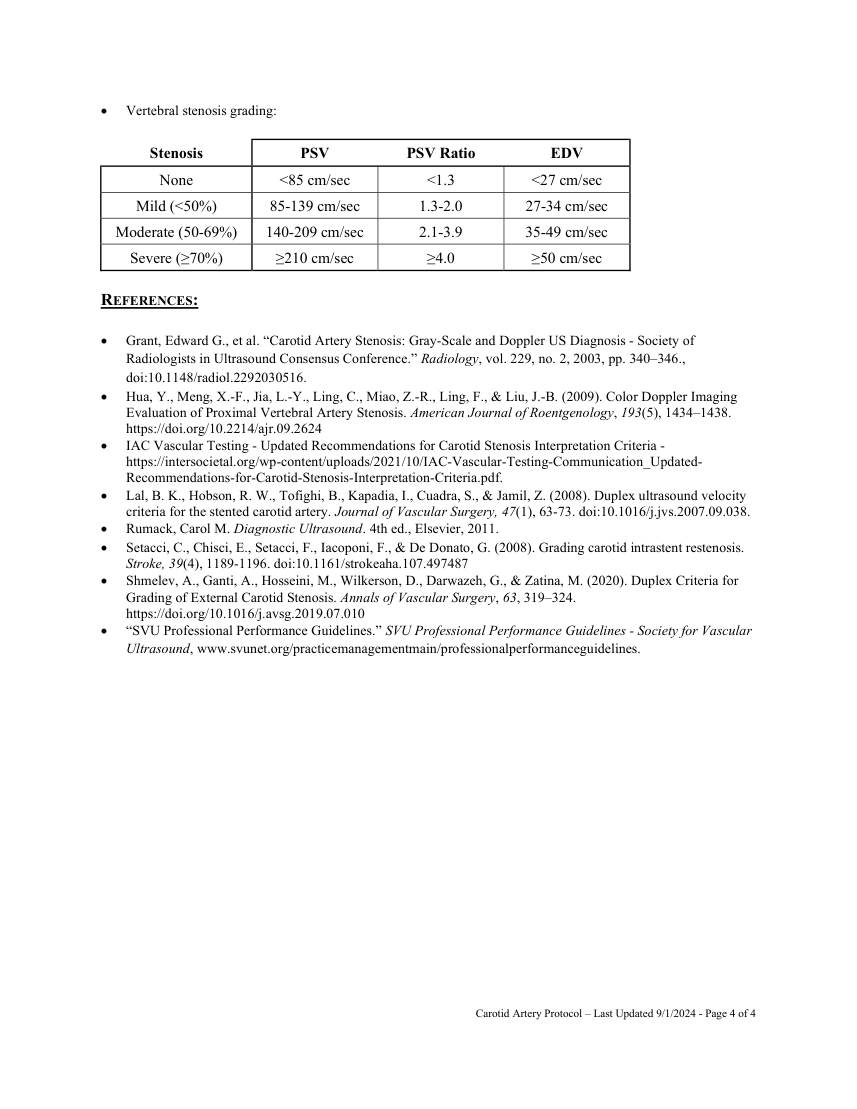
Stenosis PSV PSV Ratio EDV None <85 cm/sec <1.3 <27 cm/sec Mild (<50%) 85-139 cm/sec 1.3-2.0 27-34 cm/sec Moderate (50-69%) 140-209 cm/sec 2.1-3.9 35-49 cm/sec Severe (≥70%) ≥210 cm/sec ≥4.0 ≥50 cm/sec
REFERENCES:
Grant, Edward G., et al. “Carotid Artery Stenosis: Gray-Scale and Doppler US Diagnosis - Society of Radiologists in Ultrasound Consensus Conference.” Radiology, vol. 229, no. 2, 2003, pp. 340–346., doi:10.1148/radiol.2292030516.
Hua, Y., Meng, X.-F., Jia, L.-Y., Ling, C., Miao, Z.-R., Ling, F., & Liu, J.-B. (2009). Color Doppler Imaging Evaluation of Proximal Vertebral Artery Stenosis. American Journal of Roentgenology, 193(5), 1434–1438. https://doi.org/10.2214/ajr.09.2624
IAC Vascular Testing - Updated Recommendations for Carotid Stenosis Interpretation Criteria - https://intersocietal.org/wp-content/uploads/2021/10/IAC-Vascular-Testing-Communication_Updated- Recommendations-for-Carotid-Stenosis-Interpretation-Criteria.pdf. Lal, B. K., Hobson, R. W., Tofighi, B., Kapadia, I., Cuadra, S., & Jamil, Z. (2008). Duplex ultrasound velocity criteria for the stented carotid artery. Journal of Vascular Surgery, 47(1), 63-73. doi:10.1016/j.jvs.2007.09.038. Rumack, Carol M. Diagnostic Ultrasound. 4th ed., Elsevier, 2011. Setacci, C., Chisci, E., Setacci, F., Iacoponi, F., & De Donato, G. (2008). Grading carotid intrastent restenosis. Stroke, 39(4), 1189-1196. doi:10.1161/strokeaha.107.497487 Shmelev, A., Ganti, A., Hosseini, M., Wilkerson, D., Darwazeh, G., & Zatina, M. (2020). Duplex Criteria for Grading of External Carotid Stenosis. Annals of Vascular Surgery, 63, 319–324. https://doi.org/10.1016/j.avsg.2019.07.010
“SVU Professional Performance Guidelines.” SVU Professional Performance Guidelines - Society for Vascular Ultrasound, www.svunet.org/practicemanagementmain/professionalperformanceguidelines.
Carotid Artery Protocol – Last Updated 9/1/2024 - Page 4 of 4