Ecografie — După tiroidectomie (MCB)
Sursă și prelucrare editorială
- Proveniență
- 1 referință declarată
- Fidelitatea preluării
- Nedocumentată
- Revizuire medicală
- Nedocumentată
Referințele declarate nu confirmă singure fidelitatea preluării sau aprobarea protocolului pentru utilizare locală.
Detalii despre surse și verificări
MCB Radiology — Post Thyroidectomy
- Ediție / versiune a sursei
- Neprecizată
- Pagină / secțiune
- Pagini: 1–2
- Relația cu protocolul
- Document original importat integral; atribuirea autorilor rămâne cea din PDF.
- Data consultării
- 2026-09-27
Prelucrarea acestei pagini
- Mod de prelucrare
- Titlu și navigare în română; documentul sursă în engleză.; PDF original integral, previzualizare și text extras automat; fără completarea parametrilor clinici lipsă.
- Adaptări față de sursă
- Nedocumentate; absența evidenței nu confirmă o preluare integrală.
- Responsabil pentru prelucrare
- Neprecizat
- Atribuire existentă în pagină
- MCB Radiology (portalul sursă). Această atribuire nu identifică automat autorul sursei sau revizorul medical.
- Versiunea paginii
- mcb-d6907c5211b0
- Actualizare declarată a paginii
- 2026-09-27 — distinctă de revizuirea medicală.
Verificarea fidelității: Nedocumentată
Revizuirea medicală: Nedocumentată
Documentul original MCB — După tiroidectomie
Protocol · 2 pagini · consultat la 2026-09-27.
Descarcă PDF-ul integral · Sursa MCB · Catalogul MCB pentru această modalitate
Instrucțiunile, valorile și ilustrațiile din documentul original sunt păstrate în engleză. Titlul și navigarea sunt în română.
Pagina 1

Pagina 2
Textul documentului original
Pagina 1 — text în engleză
PURPOSE:
To evaluate for recurrent disease or regional nodal metastases after total or partial thyroidectomy for thyroid carcinoma. EQUIPMENT: 5-15 MHz linear probe PATIENT PREPARATION & ASSESSMENT: Introduce yourself to the patient.
Verify patient identity via two patient identifiers (name and date of birth) per hospital policy. Explain the exam, its purpose and how long it will take. Answer any questions the patient may have regarding the exam. Obtain patient history including symptoms, signs, risk factors and other relevant history. GENERAL GUIDELINES: Send the measurements screenshot page if your machine is capable. For focal lesions (masses, cysts, nodules, lymph nodes, fibroids) obtain examination-screen images of the lesion without calibers, with calibers and with Color Doppler.
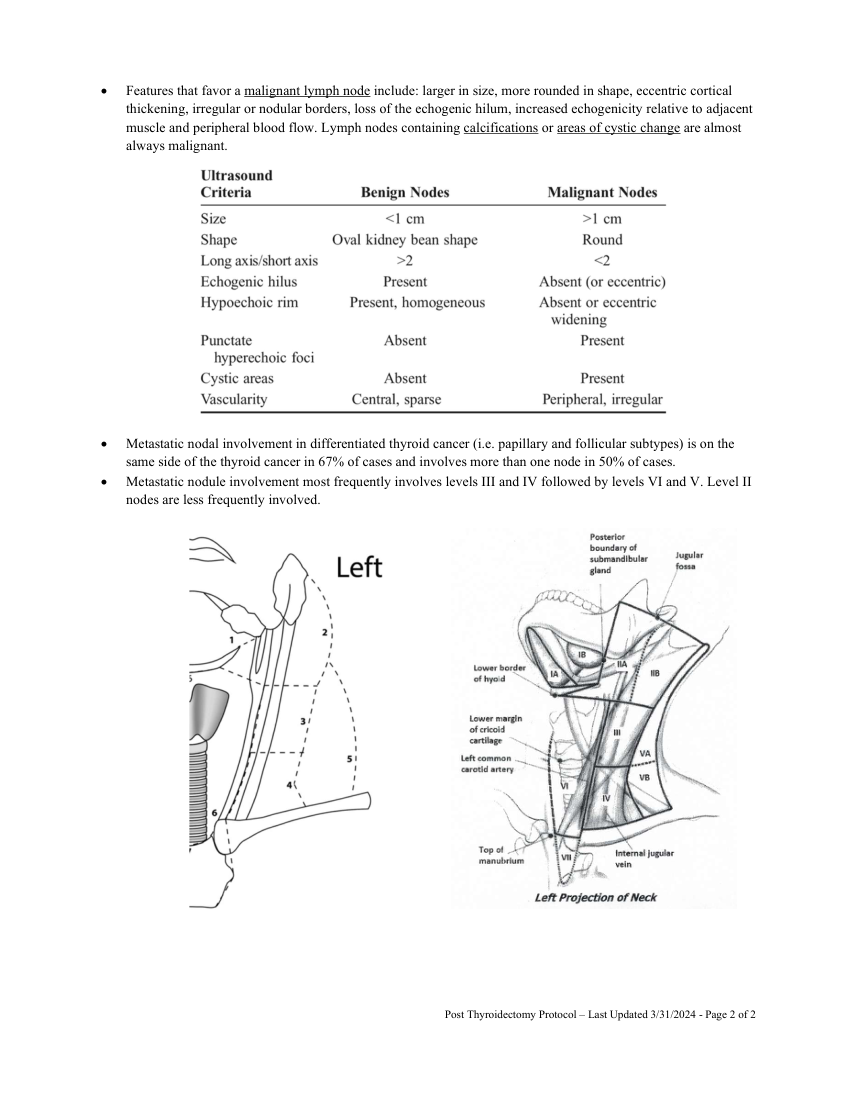
Any deviations from the standard protocol and any limitations to the examination should be documented on the technologist worksheet for future reference and for repeatability in follow-up studies. Report preliminary critical findings to the referring clinician when appropriate (i.e. immediate medical attention may be warranted) and according to hospital policy. DOCUMENTATION: Surgical Bed Document sweeping longitudinal images lateral to medial of each surgical bed. Document sweeping transverse images superior to inferior of each bed. Document grayscale images without and with 3 plane size measurements and with color Doppler flow of any residual thyroid parenchyma, nodule/mass or lymph node in the surgical bed. Cervical Nodes The technologist should document representative transverse and sagittal images of each nodal level as depicted in the below diagram (e.g. right I, right II, etc through level VI then continue with the left side).
Do NOT image and measure every normal lymph node. Measure the 1-2 largest nodes on each side of the neck, then focus on assessing for lymph nodes with suspicious features. Features that favor a benign lymph node include: less than 10 mm in short-axis and elongated or kidney bean shaped (although level II nodes can measure up to 15 mm in short-axis and be more rounded) and have a thin homogeneous hypoechoic cortex surrounding an echogenic hilum. In small nodes the echogenic hilum can be difficult to visualized, however these nodes will maintain an elongated shape. Benign nodes usually demonstrate central/hilum vascularity if detectable.
Post Thyroidectomy Protocol – Last Updated 3/31/2024 - Page 1 of 2
Pagina 2 — text în engleză
Metastatic nodal involvement in differentiated thyroid cancer (i.e. papillary and follicular subtypes) is on the same side of the thyroid cancer in 67% of cases and involves more than one node in 50% of cases. Metastatic nodule involvement most frequently involves levels III and IV followed by levels VI and V. Level II nodes are less frequently involved.
Post Thyroidectomy Protocol – Last Updated 3/31/2024 - Page 2 of 2